


Why am I always bloated is one of the most common questions in adult medicine. US surveys put the prevalence of bloating symptoms somewhere between 16% and 31% of adults, in both men and women. Bloating (the feeling) and distension (the visible change in your belly) are two different things with two different mechanisms, and the difference changes what actually helps. A large share of visible distension isn’t extra gas at all. It’s a reflex in which the diaphragm drops while the abdominal wall relaxes, pushing the belly forward. Stomach acid matters more than people realize — but not in the way the internet says. Reduced gastric acid is a documented risk factor for bacterial overgrowth in the small intestine.
Why am I always bloated? Not the occasional heavy-meal version — the daily one. Flat in the morning, visibly distended by dinner, regardless of what you ate, often with a waistband that goes from comfortable to unbearable in the space of an afternoon.
Plenty of people describe chronic bloating in exactly those terms: looking six months pregnant by evening, in a body that looked completely normal at breakfast. It’s one of the most distinctive patterns in digestive medicine, and one of the most consistently misread.
If you’re asking why am I always bloated, that pattern is not random — and it’s usually not a mystery food you haven’t identified yet.
Why am I always bloated has two separate answers, and untangling them is the whole game.
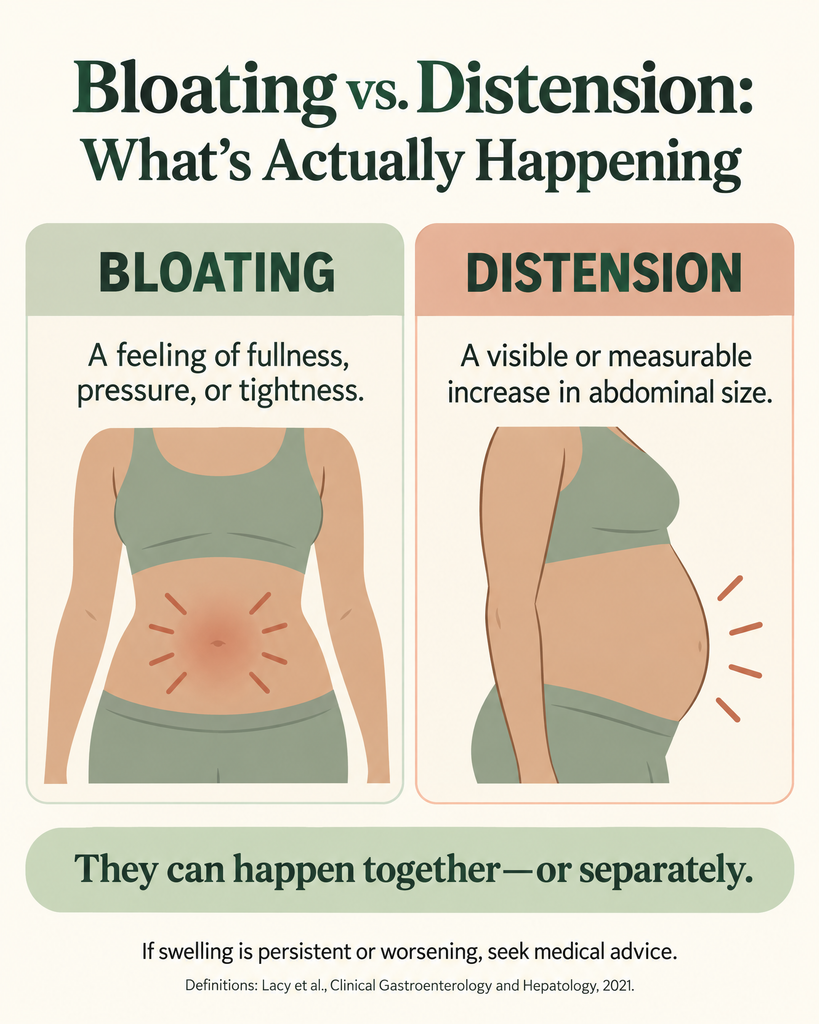
Bloating is the sensation — fullness, pressure, gassiness. It’s often driven by visceral hypersensitivity, meaning the nerves in your gut report normal volumes as uncomfortable.
Distension is the measurable change in the shape of your abdomen. Here’s the part that surprises most people: imaging studies comparing patients with healthy controls found that many people with visible distension didn’t have more gas in their intestines. What they had was a paradoxical muscle response — the diaphragm contracting downward while the abdominal wall relaxes outward. The belly pushes forward. The contents barely changed.
You may already know that certain foods produce gas. What’s less widely understood is that in most chronic cases, the food isn’t creating an abnormal amount of gas — the system is handling a normal amount badly.
Common signs of the pattern:
Flat in the morning, noticeably distended by evening Belly size changes hour to hour rather than day to day Fullness or pressure disproportionate to how much you ate A sense of incomplete emptying with bowel movements Symptoms that improve overnight and reset the next day Trapped gas that’s difficult to pass Bloating that worsens during stressful periods
Constipation and incomplete evacuation. The most common driver and the most overlooked, partly because plenty of people having a daily bowel movement still aren’t emptying well. Retained stool slows transit and impairs gas clearance, which feeds directly into distension.
Pelvic floor and anorectal coordination. When the muscles that should relax during a bowel movement contract instead, both stool and gas become hard to evacuate — and prolonged difficulty expelling gas correlates with distension symptoms.
Visceral hypersensitivity and the gut-brain axis. Heightened gut sensitivity amplifies the perception of normal volumes, and that sensation can trigger the diaphragm-and-abdominal-wall response that produces visible distension. This is also why bloating reliably worsens during stressful stretches — the gut-brain connection is bidirectional and well documented.
Food triggers and fermentation load. Certain carbohydrates — the fermentable ones grouped under the FODMAP label — ferment more in the colon, and in sensitive people that means more gas and more pressure. This is real. It’s just rarely the whole answer, and it’s rarely where the fix should start.
Gut microbial imbalance, including bacterial overgrowth. When bacteria that belong in the colon establish themselves in the small intestine, fermentation happens higher up and earlier, which produces bloating soon after eating. Reduced stomach acid is one documented contributor: a 2025 meta-analysis of 29 studies found that proton pump inhibitor use roughly doubled the risk of small intestinal bacterial overgrowth, with risk rising the longer the medication was taken.
Low stomach acid — with an honest caveat. Stomach acid is a barrier that limits how many bacteria survive the trip into the small intestine, so genuinely low acid matters. But “low stomach acid” gets diagnosed online far more often than it’s demonstrated, and the popular at-home tests — the baking soda burp test, in particular — have no validated accuracy. The meaningful version of this is acid suppression from long-term medication use, which is measurable and worth reviewing with your prescriber rather than guessing at.
“Most chronic bloating isn’t a food you haven’t found yet. It’s a motility, muscle, or sensitivity problem that food is only revealing.”
| Conventional Approach | Root-Cause Approach | |
| First step | Cut out common trigger foods | Assess transit, evacuation, and whether it’s sensation or distension |
| Focus | Reduce gas production | Improve clearance and lower gut sensitivity |
| Diet role | Long-term restriction | Structured, time-limited trial with planned reintroduction |
| Testing | Rarely beyond basic bloodwork | Targeted testing, including stool testing when there’s a specific question to answer |
| Timeline | Immediate relief, symptoms return | Weeks, with more durable change |
Stool testing comes up constantly when someone asks why am I always bloated, and it’s worth being precise about what it does and doesn’t do.
It’s genuinely useful when there’s a specific question to answer. Inflammatory markers in stool help distinguish inflammatory bowel disease from irritable bowel syndrome — a distinction that changes management entirely. Pathogen and parasite testing matters when symptoms started suddenly, followed travel, or came after a gastrointestinal infection. Markers of digestive enzyme output can point toward a pancreatic cause when symptoms include greasy stools and weight loss.
What stool testing doesn’t do is hand you a tidy microbiome report card that explains every symptom. Interpretation of broad microbial panels is still an evolving area, and no stool test replaces the basic assessment of transit, evacuation, and sensitivity.
We use it where it answers something specific — not as a default first move for everyone with a bloated belly.
1. Fix the exit before you edit the entrance. If evacuation is incomplete, everything else you try will underperform. Adequate hydration, magnesium where appropriate, a consistent morning routine, and a footstool to improve toilet posture all address clearance directly.
2. Add fiber gradually and from real food. Going from low fiber to high overnight will reliably make bloating worse for a week or two. Build slowly — cooked vegetables, oats, chia, kiwi, and beans introduced in amounts your gut can adapt to.
3. Walk after meals. Ten minutes of gentle movement after eating supports motility and gas transit. It’s unglamorous and it works better than most supplements marketed for bloating.
4. Use a low-FODMAP trial as a diagnostic, not a lifestyle. The evidence here is good — reviews find roughly half to three-quarters of people with IBS improve on it. But the value is in the reintroduction phase. In a blinded reintroduction study, responders reacted to an average of about two and a half FODMAP categories, not all of them. Most people restrict far more than they need to. Do the elimination for a few weeks, with guidance, then systematically bring foods back.
5. Slow down at the table. Eating quickly, talking while eating, drinking through a straw, and chewing gum all increase swallowed air. It sounds trivial and it’s a measurable contributor for some people.
6. Treat stress as a digestive input. The gut-brain axis runs in both directions, and bloating that flares during hard stretches is following that pathway. Slow diaphragmatic breathing before meals — a few minutes, into the lower ribs — targets both the stress response and the abdominal wall reflex behind visible distension.
7. Look upstream at what else is going on. Thyroid dysfunction slows motility. Celiac disease is underdiagnosed and worth screening before you eliminate gluten — testing becomes unreliable once you’ve already removed it. And in women, bloating that follows a monthly rhythm, worse in the second half of the cycle, points toward a hormonal driver rather than a digestive one.
The pattern that matters most, when you’re asking why am I always bloated, is persistent versus fluctuating. Research analyzing women’s symptom descriptions found that persistent abdominal distension was significantly associated with ovarian cancer, while distension that came and went was not. Guidance recommends testing when a woman — particularly age 50 or over — reports persistent or frequent bloating, early fullness or loss of appetite, or pelvic pain, especially occurring more than 12 times a month.
For anyone, seek evaluation promptly for unintentional weight loss, blood in the stool or black stools, difficulty swallowing, persistent vomiting, iron deficiency anemia, a family history of gastrointestinal cancer, new symptoms starting after age 50, or bloating that started suddenly and hasn’t let up.
Why am I always bloated when I eat healthy? Healthy and well-tolerated aren’t the same thing. A large salad, a smoothie packed with fruit, beans, and cruciferous vegetables are all excellent foods that also carry a high fermentation load. The issue is usually quantity and the speed of the increase, not the food itself.
Does bloating mean I have SIBO? Sometimes, but it’s diagnosed far more often than it’s confirmed. Breath testing has real limitations, and constipation and visceral hypersensitivity account for a much larger share of chronic bloating. Rule out the common things first.
Why am I always bloated by evening but flat in the morning? That daily arc is the classic signature of distension driven by the abdominal wall reflex rather than accumulating gas. It resets overnight because the muscle response resets.
Should I just cut out gluten and dairy? Not as a first move, and not before celiac testing — removing gluten first makes the test unreliable. Open-ended elimination tends to shrink the diet without solving the mechanism.
Do digestive enzymes or acid supplements help? They help some people, particularly where there’s a demonstrated reason to use them. Taking acid supplements on the basis of an unvalidated self-test isn’t harmless — they’re not appropriate for anyone with reflux, ulcers, or on certain medications. Worth a conversation before a purchase.
Why am I always bloated is a question that gets dismissed a lot — by other people, and eventually by the person living with it. But the mechanisms behind chronic bloating are well described and largely addressable.
“The question isn’t ‘what food is doing this to me.’ It’s ‘why has my gut become this sensitive, and why isn’t it clearing.'”
Whether this is your first visit or your next one, a real evaluation beats another round of guessing at foods.
Are You Struggling With Persistent Bloating? Our team would love to meet with you.
Click this link to schedule a time to meet with our team.
Related: Why Do I Have No Energy After Eating? | Why Your Annual Bloodwork Can Look “Normal” | Signs of Estrogen Dominance


